Purpose
Background: Interstitial lung disease (ILD) with multi-organ involvement poses substantial diagnostic challenges. ITGA3-related interstitial lung disease, nephropathy, and epidermolysis bullosa (ILNEB) syndrome is a rare autosomal-recessive condition caused by biallelic loss-of-function variants in ITGA3. Even in genetically confirmed cases, the full molecular landscape driving multi-system disease severity often remains incompletely understood, and additional genetic contributors may compound the primary diagnosis.
Case Summary: We present a 31-year-old man with confirmed compound heterozygous pathogenic/likely pathogenic ITGA3 variants [c.2070+1G>A (Pathogenic); c.1973C>G / p.(Thr658Arg) (Likely Pathogenic)] consistent with ILNEB syndrome. Although the primary genetic diagnosis has been established, his clinical presentation - encompassing progressive pulmonary fibrosis and bronchiolitis obliterans requiring continuous supplemental oxygen, prior renal transplant for fibrotic nephropathy, ectodermal abnormalities, gastrointestinal dysmotility, and salivary gland involvement - raises the possibility that other genomic variants may further modulate disease expression. This warrants broader multi-omic investigation beyond the known ITGA3 genotype.
Molecular Findings: Whole genome sequencing (WGS) via PacBio long-read technology, combined with HPO-guided variant prioritization (SEQ™ platform), identified 10 small variants and 15 structural variants across five convergent biological modules: (1) epithelial adhesion/barrier integrity (ITGA3, PLEC, MUC1, MUC5B, ABCA3, SLC34A2, PKHD1); (2) TGF-β/fibrosis signaling (STAT3); (3) immune remodeling (STAT6, STAT4, IRF4); (4) antigen presentation/inflammatory regulation (HLA-B, HLA-DRB1, HLA-DQB1, C4A, IL1RN, IKBKG); and (5) telomere maintenance (TERT, POT1). Single-cell RNA sequencing (scRNA-seq) of patient PBMCs, followed by SigCom-LINCS connectivity analysis across multiple perturbational databases, demonstrated partial concordance between patient-specific gene expression signatures and the WGS-nominated modules - particularly for the TGF-β, telomere, and HLA-related axes.
Clinical Implications: These findings suggest that the patient’s multisystem phenotype may reflect convergent genetic vulnerabilities beyond ITGA3 alone. The TERT/POT1 telomere module and TGF-β/SMAD signaling axis are especially relevant given their established roles in fibrotic ILD. All variants remain classified as VUS or VUS+ and require functional and clinical validation. This case illustrates the potential value of symptom-guided multi-omic workflows as a complement to established genetic diagnoses in molecularly complex rare diseases.
Important Notice: This document is intended for research purposes only and does not constitute a clinical diagnosis.
Introduction
ITGA3-related ILNEB syndrome is an ultra-rare autosomal-recessive disorder in which biallelic loss-of-function variants in ITGA3 (encoding integrin subunit alpha-3, a key mediator of epithelial cell adhesion to laminin-332 in the basement membrane) result in a triad of interstitial lung disease, nephrotic syndrome/nephropathy, and epidermolysis bullosa1–2. The disorder is mechanistically driven by failure of the α3β1 integrin heterodimer to maintain epithelial integrity across multiple organ systems. Fewer than 30 cases have been reported in the literature, and the disease course is often severe and progressive, with lung disease being the principal driver of morbidity and mortality1, 3–4.
Interstitial lung diseases more broadly remain diagnostically and therapeutically challenging. Standard antifibrotic agents - pirfenidone and nintedanib - have demonstrated efficacy in idiopathic pulmonary fibrosis (IPF) but are associated with significant gastrointestinal adverse effects that limit tolerability, particularly in patients with pre-existing GI involvement5–6. Nerandomilast (Jascayd), a selective oral phosphodiesterase 4B (PDE4B) inhibitor, has emerged as an alternative antifibrotic approach with a distinct mechanism and potentially improved GI tolerability profile, and has been evaluated for ILD including IPF7.
Even in genetically confirmed cases of ILNEB, the full molecular complexity of disease may not be entirely attributable to the primary ITGA3 genotype. Additional rare variants in fibrosis-related genes, telomere biology genes, and immune-regulatory loci could modulate disease severity and multi-organ involvement. Short-read sequencing technologies, although powerful for SNV detection, have inherent limitations in resolving structural variants (SVs), repeat-mediated rearrangements, and challenging genomic loci such as HLA. Long-read whole genome sequencing (WGS) using PacBio HiFi chemistry substantially improves SV detection accuracy, enables phasing of compound heterozygous variants, and provides more reliable coverage of complex genomic regions - offering the potential to uncover additional pathogenic contributors that may be missed by conventional approaches8. Many candidate variants, even in well-established disease genes, remain classified as variants of uncertain significance (VUS); more comprehensive sequencing approaches may help build supporting evidence for their biological relevance.
Complementing genomic discovery with transcriptomic profiling provides an orthogonal perspective on which biological pathways are engaged in the patient. The Human Phenotype Ontology (HPO) offers a standardized vocabulary for encoding clinical phenotypes, enabling computational phenotype-to-genotype matching and variant prioritization9. The Connectivity Map (CMap) and its expanded implementation via SigCom-LINCS provide a framework for comparing patient gene expression signatures against a large reference compendium of perturbational profiles (gene knockdowns, overexpressions, and small molecule treatments), enabling hypothesis generation about which biological pathways are engaged10–13. Together, long-read WGS and scRNA-seq-based transcriptomic fingerprinting constitute an integrated multi-omic strategy that may help contextualize molecular findings beyond the primary ITGA3 diagnosis.
Here, we present a symptom-guided multi-omic investigation of a patient with genetically confirmed ITGA3-related ILNEB syndrome but with clinical complexity suggesting additional molecular contributors. We apply HPO-driven long-read WGS variant prioritization and scRNA-seq transcriptomic fingerprinting with SigCom-LINCS connectivity analysis to identify convergent pathogenic modules and assess their concordance across genomic and transcriptomic data layers.
Case Presentation
The patient is a 31-year-old man with genetically confirmed compound heterozygous ITGA3 variants causing ILNEB syndrome. The ITGA3 genotype comprises: (A) a canonical splice donor variant at intron 15 [NM_002204.4(ITGA3):c.2070+1G>A; classified Pathogenic per ACMG criteria PVS1+PM2+PP5], which predicts loss-of-function through exon skipping, frameshift, premature stop, and nonsense-mediated decay (null allele); and (B) a missense variant in exon 15 [NM_002204.4(ITGA3):c.1973C>G; p.(Thr658Arg); classified Likely Pathogenic per ACMG criteria PM1+PM2+PP3+PP5], located within the integrin alpha-2/alpha-domain superfamily and predicted by multiple in silico tools (CADD 25.6, SIFT deleterious, PolyPhen-2 probably damaging) to impair protein folding/trafficking (hypomorphic allele). The compound heterozygous combination predicts a marked reduction in functional α3β1 integrin, consistent with the EB-ILNEB spectrum documented in ClinVar (Variation IDs 209163 and 209162).
Renal History
Renal involvement has been a defining feature of his illness. He has an established history of renal fibrosis with asymmetric kidney hypoplasia. In 2014, he underwent living-related donor kidney transplantation without complications and without subsequent acute or chronic rejection episodes. He is maintained on chronic post-transplant immunosuppression with tacrolimus (1 mg twice daily) and mycophenolic acid (360 mg twice daily).
Pulmonary Disease
Pulmonary disease is the primary determinant of current morbidity. He has severe, progressive lung disease characterized by extensive pulmonary fibrosis, obstructive and constrictive bronchiolitis (bronchiolitis obliterans), and chronic respiratory failure requiring continuous supplemental oxygen. Retrospective review of high-resolution CT imaging dating to 2016 documents progressive worsening through 2019, with more stable radiologic findings since 2024. Quantitative CT with parametric response mapping (PRM; February 2026) demonstrates a combination of consolidative opacities and air trapping, with functional small-airway disease quantified at 8% of total lung volume.
Pulmonary function testing at Stanford Medicine (October 2025) confirmed severe mixed restrictive and obstructive limitation: FVC 1.64 L (37.1% predicted), FEV₁ 0.92 L (24.8% predicted), and DLCO 12.54 mL/min/mmHg (42.5% predicted). Given progressive symptoms and declining functional status, he underwent lung transplantation evaluation in July 2025. Immunological profiling of peripheral blood mononuclear cells (PBMCs) by regulatory T (Treg) cell-specific demethylated region (TSDR) analysis demonstrated a reduced number of T regulatory (Treg) cells, consistent with immune dysregulation.
Pathology
Lung wedge resection (upper lobe) demonstrates a chronic graft-versus-host disease (cGVHD)-like bronchiolitis obliterans syndrome (BOS) phenotype, characterized by bronchiolitis obliterans and lymphocytic bronchiolitis with associated lymphoid aggregates. Serial resections document clear progression: the 2017 biopsy showed predominantly subepithelial fibrosis with lymphocytic bronchiolitis, while the 2022 biopsy demonstrates complete obliteration of many bronchioles, with residual bronchioles showing subepithelial fibrosis and luminal macrophages and debris. The alveoli are largely spared. Multiplexed immunofluorescence analysis (Akoya Biosciences PhenoCode IO60 Panel) confirms marked proliferation of macrophages (CD68), particularly M2-polarized macrophages (CD163, CD206), indicative of an ongoing pro-fibrotic inflammatory response.
Minor salivary gland biopsy (buccal mucosa, February 2026) provides further histologic evidence of systemic cGVHD-like involvement, demonstrating fibroinflammatory stromal change with 80-90% fibrofatty replacement of salivary gland tissue in two of three glands, and characteristic cytoplasmic vacuoles in duct epithelium with intraepithelial lymphocytes in the third gland. These findings are consistent with systemic fibroinflammatory disease extending beyond lung and kidney.
Pharmacological History and Current Management
Prior trials of antifibrotic therapy - including an antifibrotic agent in the pirfenidone/nintedanib class - were associated with marked worsening of pre-existing gastrointestinal symptoms, limiting tolerability and precluding continued use. Nerandomilast (Jascayd; 18 mg twice daily), an oral selective PDE4B inhibitor, was subsequently initiated and was better tolerated from a GI standpoint; however, as of March 2026 it has not demonstrated clear clinical efficacy. Other recent medications include: amlodipine (5 mg QD), beclomethasone (inhaled, BID), budesonide (nebulized, 1 mg BID), formoterol (nebulized, 20 mcg BID), losartan (100 mg QD), omeprazole (40 mg QID), sotatercept (subcutaneous Q3.5W), teriparatide (subcutaneous QD), and tiotropium (2 puffs QD).
HPO Encoding for Computational Variant Prioritization
Clinical phrases documented by the treating physician were systematically mapped to 22 standardized HPO terms (Table 1), enabling computational phenotype matching and variant prioritization within the SEQ™ platform14–16.
| Clinical Phrase (from the patient’s physician) | HPO Term | HPO ID |
|---|---|---|
| Shin rash in childhood | Skin Rash | HP:0000988 |
| Residual skin scarring | Scarring | HP:0100699 |
| Low enamel / enamel defect | Enamel hypoplasia | HP:0006297 |
| Shortness of breath | Dyspnea | HP:0002094 |
| Worsening dyspnea on exertion | Exertional dyspnea | HP:0002875 |
| Lung fibrosis | Pulmonary fibrosis | HP:0002206 |
| Airway inflammation / bronchiolitis | Bronchiolitis | HP:0011950 |
| Severe small-airway scarring | Bronchiolitis obliterans | HP:0011946 |
| Pneumothorax | Pneumothorax | HP:0002107 |
| Chest pain during pneumothorax | Chest pain | HP:0100749 |
| Reduced lung function | Abnormal PFT | HP:0030878 |
| Kidney fibrosis / scarred kidney | Renal fibrosis | HP:0030760 |
| Asymmetric kidney size | Small kidney (unilateral) | HP:0000089 |
| Progressive kidney disease | Progressive renal insufficiency | HP:0012622 |
| Esophageal dysmotility | Esophageal spasms | HP:0025271 |
| Nausea | Nausea | HP:0002018 |
| Chronic diarrhea | Chronic diarrhea | HP:0002028 |
| Low body weight | Low body weight | HP:0004325 |
| Slender build | Slender build | HP:0001533 |
| Osteopenia | Osteopenia | HP:0000938 |
| Pulmonary infiltrates | Pulmonary infiltrates | HP:0002113 |
| Recurrent pneumonia | Pneumonia | HP:0002090 |
Table 1. HPO Term Mapping from Clinical Presentation
Results: Molecular Analysis and Interpretation
The analysis was structured in two sequential but complementary parts (Image 1). Part I applied long-read WGS followed by HPO-driven phenotype filtering and variant prioritization using the SEQ™ platform. Part II leveraged scRNA-seq-derived gene expression fingerprints from patient PBMCs and cross-referenced them against SigCom-LINCS perturbational databases, enabling assessment of transcriptomic concordance with the genomic findings.
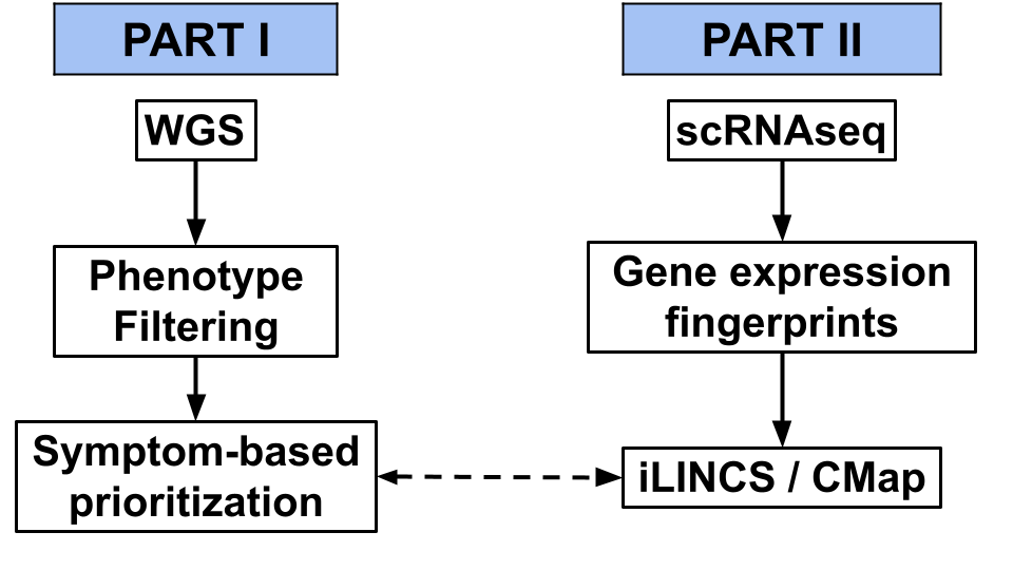
Figure 1. Two-part multi-omic analysis workflow. Part I: PacBio long-read WGS with HPO-guided phenotype filtering and SEQ™-based variant prioritization. Part II: scRNA-seq PBMC profiling with SigCom-LINCS connectivity analysis. The dashed arrow indicates the cross-validation step between genomic and transcriptomic findings.
Part I: Whole Genome Sequencing and Variant Prioritization
For the first part of the analyses, PacBio long-read HiFi WGS was performed on patient-derived samples. The SEQ™ bioinformatics platform was used for variant calling, annotation, and multi-step filtering. HPO terms derived from the clinical narrative (Table 1) were entered into the platform to restrict candidates to phenotypically concordant variants. Prioritization tiers, population allele frequency filtering (<1% in healthy populations), and consequence filters (destructive/exonic) were applied as described previously14–18.
Small Nucleotide Variants (SNVs and Indels)
After HPO-guided filtering, 10 high-priority small variants were identified across clinically relevant genes (Table 2). All variants were classified as VUS or VUS+. Of note, MUC1 carries a homozygous (HM) splice donor variant, and HLA-DRB1 shows complex compound zygosity (HT, HM, and cHT). TERT (8 HPO matches) and HLA-DRB1 (11 HPO matches) exhibited the highest phenotype concordance. ITGA3 itself emerged in the WGS analysis with the previously characterized compound heterozygous genotype. The full extended SNV list with allele frequencies and additional annotation is provided in Supplementary Table 1.
| Gene | Variant Type | ACMG | Phenotype Matches | Genotype |
|---|---|---|---|---|
| TERT | Missense Variant | VUS | 8 | HT |
| HLA-B | Missense Variant (×2 alleles) | VUS | 7 | HT |
| STAT6 | Inframe Deletion | VUS+ | 3 | HT |
| AFF3 | Inframe Deletion | VUS+ | 3 | HT |
| MUC1 | Splice Donor Variant | VUS+ | 3 | HM |
| C4A | Missense/Splice Region/Intron Variants | VUS | 3 | HT |
| HLA-DRB1 | Splice Donor Region/Intron Variant | VUS | 11 | HT, HM, cHT |
Table 2. High-Priority Small Variants Identified by HPO-Filtered WGS
ACMG classification shown; VUS+ indicates variants with additional supporting evidence. HT: heterozygous; HM: homozygous; cHT: compound heterozygous.
Structural Variants (SVs)
Targeted long-read variant calling identified 15 structural variants, predominantly deletions (DEL), across genes with clinical relevance (Table 3). Notable findings include intronic deletions in STAT3 (10 HPO phenotype matches), SLC34A2 (7 phenotype matches, with the deletion spanning Exon 1), ABCA3 (7 matches), and IRF4 (7 matches). A MUC5B deletion in Exon 37 and a PKHD1 intronic deletion (6 HPO matches) were also identified - the latter potentially contributing to the renal phenotype given PKHD1’s known role in polycystic kidney disease and ductal epithelial integrity. A targeted caller for the complement factor H (CFH) locus identified a haplotype 2 deletion (chr1:196757557-196760029 and chr1:196842234-196844710), potentially implicating complement dysregulation. The complete phenotype-to-variant overlap mapping (indicating which specific HPO terms match for each variant) is provided in Supplementary Table 2.
| Gene | Position | SV Type | Transcript / Location | ACMG | HPO Matches |
|---|---|---|---|---|---|
| STAT3 | chr17:42332391-42332695 (305 bp) | DEL | ENST00000264657, Intron 10 | VUS | 10 |
| PKHD1 | chr6:52051813-52051854 (42 bp) | DEL | ENST00000371117, Intron 21 | VUS | 6 |
| SLC34A2 | chr4:25648086-25648121 (36 bp) | DEL | ENST00000645788, Exon 1 | VUS | 7 |
| IL1RN | chr2:113130557-113130727 (171 bp) | DEL | ENST00000409930, Intron 2 | VUS | 6 |
| PLEC | chr8:143931281-143931393 (113 bp) | DEL | ENST00000345136, Intron 19 | VUS | 6 |
| SLC9A3 | chr5:474426-474795 (370 bp) | DEL | ENST00000264938, Intron 16 | VUS | 5 |
| POT1 | chr7:124919976-124920010 (35 bp) | DEL | ENST00000357628, Intron 2 | VUS | 3 |
| MUC5B | chr11:1255551-1255668 (118 bp) | DEL | ENST00000529681, Exon 37 | VUS | 4 |
| STAT4 | chr2:191141407-191141454 (48 bp) | DEL | ENST00000392320, Intron 3 | VUS | 6 |
| IRF4 | chr6:396779-397055 (277 bp) | DEL | ENST00000380956, Intron 4 | VUS | 7 |
| NDUFAF6 | chr8:95091014-95091051 (38 bp) | DEL | ENST00000523184, Intron 2 | VUS | 5 |
| ERCC6 | chr10:49507921-49507960 (40 bp) | DEL | ENST00000355832, Intron 5 | VUS | 6 |
| HLA-DQB1 | chr6:32662524-32662563 (40 bp) | DEL | ENST00000434651, Intron 2 | VUS | 6 |
| ABCA3 | chr16:2299155-2299205 (51 bp) | DEL | ENST00000301732, Intron 14 | VUS | 7 |
| PRTN3 | chr19:841535-841618 (84 bp) | DEL | ENST00000234347, Intron 1 | VUS | 6 |
Table 3. Structural Variants Identified by Long-Read WGS
Part II: Single-Cell RNA Sequencing and Transcriptomic Fingerprinting
To complement the genomic findings, scRNA-seq was performed on patient PBMCs and compared against a healthy control sample. Dimensionality reduction (UMAP) resolved eight major immune cell populations: NK cells, monocytes, T cells, CD4+ T cells, CD8+ T cells, B cells, dendritic cells, and neutrophils (Image 2A).
Per-cluster differentially expressed genes (DEGs) were computed between patient and healthy control samples across four major immune compartments: T cells, B cells, NK cells, and monocytes. Upregulated and downregulated gene sets from each cluster were submitted as independent queries to the SigCom-LINCS API19, querying multiple perturbational L1000 databases (l1000_cp, l1000_mean_cp, l1000_oe, l1000_xpr, l1000_mean_xpr, l1000_lig, l1000_aby, and l1000_shRNA). Retrieved perturbational signatures were filtered using the following criteria: exemplar status, |z-sum| ≥ 2, and p < 0.05 (either direction). An additional biological relevance filter was applied to retain signatures originating from tissues relevant to this case (blood, bone marrow, lymphoid tissue, lung, connective tissue, epithelium, kidney), from cell lines representative of immune and pulmonary biology (including JURKAT, THP1, U937, A549, NL20, AALE, among others), or from disease contexts including leukemia, lymphoma, and lung cancer. Perturbations appearing in matched results from at least two cell-cluster comparisons (e.g., appearing in both monocyte and NK cell DEG queries) were preferentially retained, to identify signals with cross-population reproducibility. The full SigCom-LINCS perturbation results are provided in Supplementary Table 3. A final cross-reference filter was applied using WGS-nominated candidate genes to identify perturbations directly implicating those genes, enabling convergent evaluation across the two data layers. Analysis code is publicly available at https://github.com/ymnmurat/itga3-lung-fibrosis-scrnaseq-ilincs.
Gene expression fingerprints comparing patient to healthy sample across all four immune cell populations presented differential expression patterns for multiple WGS-nominated candidates (Image 2B; Supplementary Table 4). Key observations included upregulation of LAMA1, TGFB1, TGFBR1, SMAD2, and SMAD4 in patient immune cells compared to the healthy control, and differential expression of HLA locus genes across B cell and monocyte compartments. These patterns across all DEGs for each cell cluster were used to generate the SigCom-LINCS query signatures.
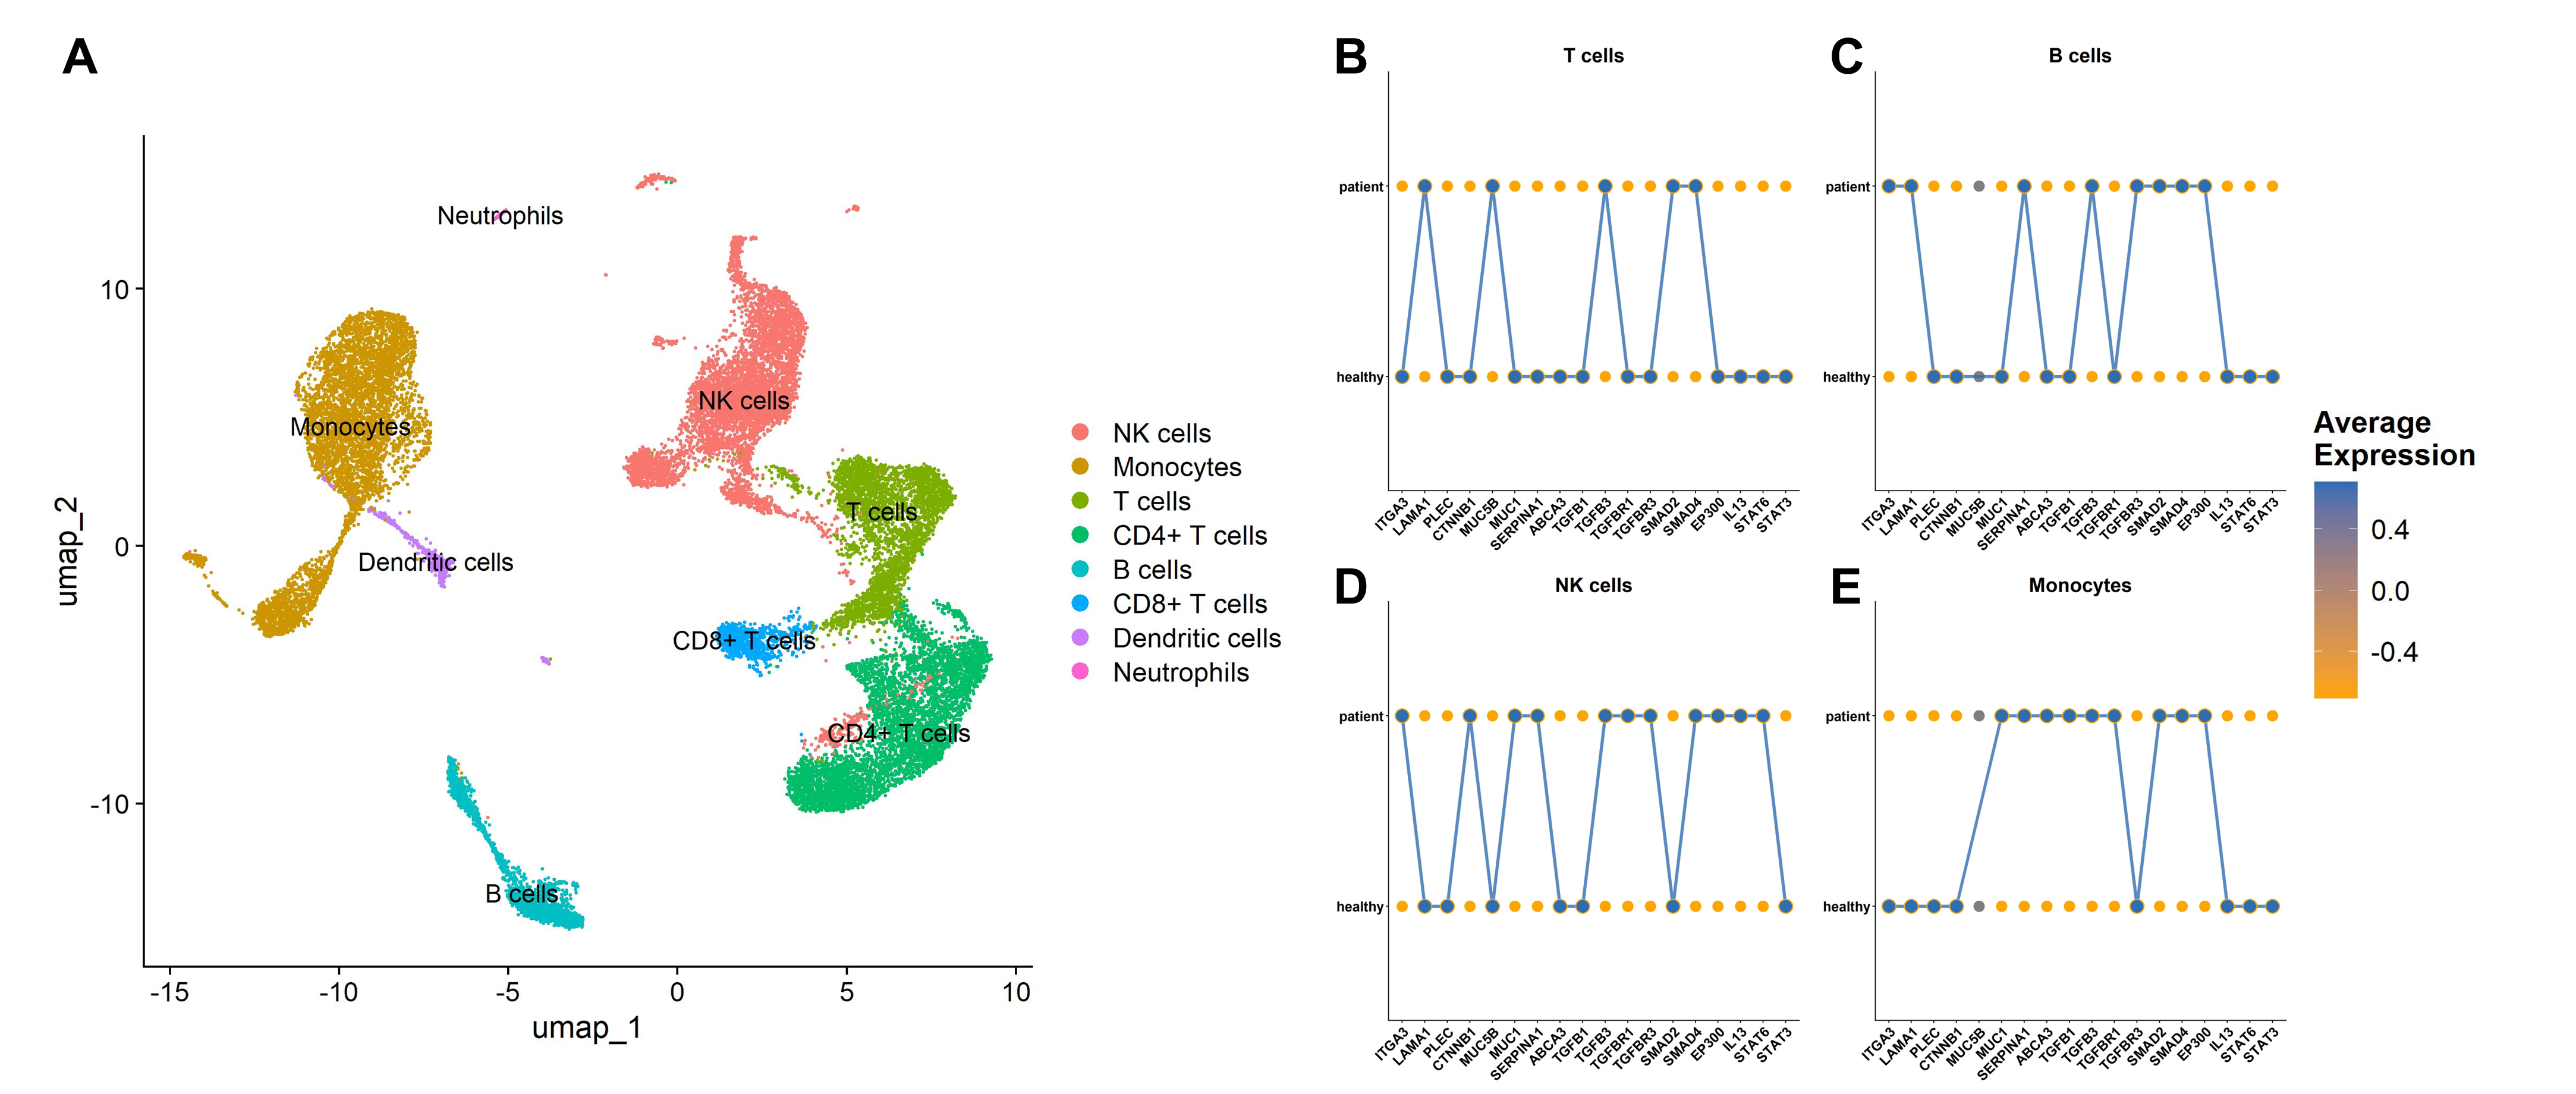
Figure 2. *(A) UMAP visualization of single-cell RNA-seq data from patient PBMCs, presenting eight major immune cell populations used as the basis for per-cluster transcriptomic fingerprinting. (B-E) Gene expression fingerprints across four major immune cell populations (T cells, B cells, NK cells, Monocytes, respectively), comparing average expression between patient and healthy control for WGS-prioritized candidate genes. Only a selected number of genes are shown and overexpressed genes are connected with lines representing a pseudo-signature for representative purpose illustrating gene expression profile differences between cell clusters. A full list of DEGs across each cell cluster that is queries in SigCom-LINCS is available in Supplementary Table 4. Blue indicates higher average expression level of a given gene; orange indicates lower. *
Discussion
This case illustrates a multi-system fibrotic disease which is studied beyond its primary genetic diagnosis. Although compound heterozygous ITGA3 variants have been confirmed as the underlying cause of this patient’s ILNEB syndrome, the ITGA3 variations alone can not explain the severity and breadth of his multi-organ involvement. ILNEB syndrome is itself rare, with fewer than 30 cases in the literature11, and its natural history, particularly regarding immune-mediated lung inflammation, remains incompletely described. The progressive BOS-like pathology with lymphoid aggregates, marked M2 macrophage expansion (CD163, CD206), and reduced peripheral Treg numbers observed in this patient are not canonical features of ITGA3-driven epithelial dysfunction, raising the question of whether additional molecular contributors modulate disease severity. The symptom-guided multi-omic approach applied here offered as one exploratory framework for examining this question.
Cross-referencing WGS-nominated candidates with SigCom-LINCS transcriptomic connectivity data revealed areas of overlap across five biological modules (Table 4). Some of the candidate genes were observed in both the WGS variant list and the SigCom-LINCS perturbational support, representing a degree of cross-dataset concordance. These include MUC1 in the epithelial module; STAT3 in the fibrosis signaling module; STAT6 in the immune remodeling module; HLA-B, HLA-DRB1, and HLA-DQB1 in the antigen presentation module; and TERT and POT1 in the telomere module. Additional SV candidates from Table 3 - PKHD1 (renal epithelial barrier), SLC34A2 (surfactant homeostasis), SLC9A3 (epithelial ion transport), AFF3 (immune modulation), and ERCC6 (DNA repair/aging) - map internally to these same modules, though their individual contributions remain speculative without functional data.
| WGS Hits | SigCom-LINCS Support | Biological Module | Proposed Follow-up |
|---|---|---|---|
| ITGA3, PLEC, MUC1*, MUC5B, ABCA3* | LAMA1, MUC1*, CTNNB1* | Epithelial adhesion / basement membrane / barrier integrity | ITGA3/laminin-332 axis; integrin-ECM interaction |
| STAT3 | TGFBR1, STAT3*, SMAD2, SMAD4, TGFB1* | TGF-β / wound repair / fibrosis signaling | pSMAD2/3 modulation; TGFBR expression profiling |
| STAT6*, STAT4, IRF4* | STAT6*, IL4, IL13, EP300* | Immune remodeling / Th2-Treg skewing | pSTAT6; IL-4/IL-13 pathway markers |
| HLA-B*,* HLA-DRB1*,* HLA-DQB1*, C4A, PRTN3, RELT, IL1RN, IKBKG* | HLA-B*,* HLA-DRB1*,* HLA-DQB1*, C4A, PRTN3, RELT, IKBKB, TAPBP, CIITA, B2M* | Antigen presentation / inflammatory regulation | NF-κB activation; complement/cytokine markers |
| TERT*,* POT1 | TERT*,* POT1 | Telomere maintenance / immune senescence | Telomere length assays; TERT/POT1 interaction |
Table 4. Concordance Between WGS Hits and SigCom-LINCS Transcriptomic Profiles
Bold gene names indicate direct one-to-one matches between the two datasets.
Among the biological modules identified, the TERT/POT1 telomere axis is the most mechanistically coherent in the context of the patient’s lung phenotype19–21. Heterozygous TERT variants are found in 8-15% of familial IPF cases and impair alveolar epithelial regeneration by accelerating cellular senescence, a mechanism that could compound primary epithelial vulnerability caused by ITGA3 loss4, 12. POT1, which protects single-stranded telomeric overhangs and whose disruption accelerates telomere attrition22, appears here as an intronic structural deletion co-occurring with the TERT variant. Whether these variants jointly alter telomere function in this patient remains to be determined by telomere length measurement and functional assays. Similarly, the HLA locus findings, including HLA-DRB1 (11 HPO matches, complex zygosity), HLA-B, and HLA-DQB1, are relevant given established associations between specific HLA haplotypes and susceptibility to immune-mediated ILD and BOS-like phenotypes23. The marked M2 macrophage expansion (CD163, CD206) on lung immunofluorescence, combined with STAT6 and IL-4/IL-13 perturbational connectivity signals, further raises the question of whether Th2 axis dysregulation contributes to the BOS-like pulmonary pathology; this hypothesis could be interrogated through cytokine profiling of bronchoalveolar lavage or patient-derived immune cell functional studies. The TGF-β/SMAD axis (STAT3, with direct one-to-one cross-dataset matches) is a well-characterized driver of fibrotic remodeling24, and pSMAD2/3 expression profiling in patient tissue could help substantiate pathway engagement; however, any therapeutic inference from this observation would require careful preclinical evaluation, given the broad and context-dependent physiological roles of TGF-β. Beyond these modules, variants in co-functioning epithelial integrity genes (PLEC, MUC1, ABCA3) may compound baseline ITGA3-mediated vulnerability. If available, this can be tested by using patient-derived organoids or airway epithelial models expressing the identified variants. Taken together, standard antifibrotic therapy with nerandomilast was the most recent medication but has not demonstrated clear efficacy, underscoring the need for mechanistic insight to inform future therapeutic strategies for similar conditions.
Several methodological limitations bear directly on the interpretation of these signals. The analysis is based on a single patient compared to a single healthy control, and inter-individual variability in immune gene expression is substantial25–28. This critically limits the ability to distinguish disease-associated transcriptomic signals from background variation. Importantly, no sensitivity analyses - such as permutation testing29–30, matched-universe analysis31–32, or removal of pleiotropic genes with high general connectivity33–34 - were performed to assess whether the observed SNV/SV overlaps with scRNA-seq signatures exceed random expectation given variant burden and panel sizes. Given the large dimensionality of both WGS and SigCom-LINCS datasets10, some degree of nominal overlap would be expected by chance35–36; the descriptive SNVs and SVs across symptom-guided panels (which are prone to phenotypic selection biases37) should therefore be considered hypothesis-generating rather than statistically validated findings. The SigCom-LINCS perturbational profiles are predominantly derived from in vitro cancer cell lines (e.g., JURKAT, THP1, A549) under experimentally perturbed conditions, which may not reflect the transcriptional state of primary immune or lung epithelial cells in this patient10, 13. Furthermore, the scRNA-seq analysis was limited to circulating PBMCs, which do not capture the cellular environment of the fibrotic lung. Moreover, immune clusters in this study were analyzed at broad resolution; for example, the T cell cluster encompasses Tregs, CD4+, and CD8+ subsets in aggregate, and higher-resolution subclustering - particularly relevant given the documented Treg reduction - was not performed. VUS classifications also rely on variant annotation databases (ClinVar, gnomAD) that may underrepresent rare alleles across diverse populations, and interpretation of complex structural variants carries inherent uncertainty related to alignment tool performance38.
Most prioritized variants remain VUS or VUS+, and none of the WGS-identified variants beyond the confirmed ITGA3 genotype are not clinically actionable in their current state. As established by ACMG/AMP guidelines, VUS classification requires orthogonal evidence - including Sanger confirmation, segregation in affected family members, and ideally functional studies - before clinical reporting15. None of these have been performed for the additional candidates identified here. To test the current findings, several complementary studies are warranted: (i) evaluating additional ILNEB or multi-system ILD patients to assess whether candidate VUS variants recur across independent cases; (ii) if any available, conducting functional validation using patient-derived iPSCs, organoids, or primary airway epithelial cells expressing the identified variants; (iii) extending onto other omics resources including single-cell profiling or available spatial transcriptomics of patient lung tissue to map fibrotic and inflammatory populations in situ; and (iv) applying formal statistical approaches (permutation testing, gene set enrichment analysis with appropriate background models) to quantify the significance of WGS–transcriptomics concordance. Deeper interrogation of structurally complex loci (particularly, the HLA region and CFH) through phased long-read sequencing with rigorous population benchmarking would also refine variant interpretation. Taken together, symptom-guided multi-omic workflows of the kind described here offer a structured approach for prioritizing phenotype-aligned candidate variants for follow-up evaluation in rare, diagnostically complex diseases. The workflow here, by itself, does not serve as a substitute for clinical or functional evidence, but as a first-pass hypothesis generation layer that may help direct subsequent investigation across similar cases.
Conclusion
In this case report, we present a symptom-guided multi-omic analysis of a patient with genetically confirmed ITGA3-related ILNEB syndrome and a complex, progressive multisystem disease course. Five biological modules emerged from the integrated analysis (epithelial integrity, TGF-β/fibrosis signaling, immune remodeling, antigen presentation, and telomere maintenance), with candidate VUS and VUS+ variants identified in each. Partial concordance between WGS-nominated genes and SigCom-LINCS perturbational support - most reproducibly for STAT3, STAT6, HLA-B, HLA-DRB1, TERT, and POT1 - provides biological plausibility to these modules but does not establish causality. The cGVHD-like pathological phenotype, reduced Treg population, and systemic fibroinflammatory involvement suggest that disease expression in this patient may not be fully explained by ITGA3 loss alone.
All findings beyond the confirmed ITGA3 genotype are hypothesis-generating and are not clinically actionable for similar cases without orthogonal validation, including functional studies, segregation analysis, and expanded cohort evaluation. Symptom-guided multi-omic workflows nonetheless offer a translational value as a complementary layer to standard genomic interpretation in rare, multi-system diseases. Accordingly, such approaches could provide a personalized, phenotype-anchored route toward prioritizing candidate variants for downstream investigation in cases where a single genetic diagnosis fails to account for the full clinical picture.
Be the first to comment on this publication.